


Pain in one breast, or in both?
Dr Jérémie Zeitoun, surgical oncologist and breast surgeon, sees patients at the practice at 241 rue du Faubourg Saint-Honoré (Paris 8e) and at Clinique Hartmann (Neuilly-sur-Seine). He examines the breast and goes through the tests you already have.
Something found on your work-up?
An examination or a scan that shows something?
For pain, your general practitioner, midwife or gynecologist comes first. If their examination or your imaging shows a lump, a cyst or an image that needs analysing, Dr Zeitoun, surgical breast oncologist, consults at the practice in central Paris and at Clinique Hartmann in Neuilly, where he operates. Consultations in English. Book an appointment or request a call back.
Breast pain, or mastalgia, is any pain felt in one or both breasts. It is very common — around 70% of women experience it at some point in their lives [1] — and, contrary to the worry it almost always causes, it is not a sign of breast cancer.
The figures are consistent from one series to the next. Among women who consult for breast pain, cancer is found in 2 to 7% of them [1]. And when pain is the only symptom, with no lump and no clinical abnormality, that figure falls to 0.8% in a Canadian series of 953 patients [2] and to 0.4% in a British cohort of 10,830 women [3] — the same level as in a screened population with no symptoms at all. For comparison, in that same cohort a lump was associated with cancer in around 5% of cases [3].
So the question is not how badly it hurts — severe cyclical pain is still cyclical pain — but how the pain behaves: does it follow the cycle or not? Does it affect both breasts or only one? Is it diffuse, or always in the same spot? Is it on its own, or alongside another sign?
This page explains how to tell the difference, goes through every cause — hormonal, within the breast, and outside it — sets out the seven situations that call for a prompt opinion, describes the work-up step by step (mammogram, ultrasound, biopsy), and covers the uncommon situations in which surgery becomes useful.
Has your work-up shown something?
An image graded BI-RADS 3, 4 or 5, a cyst, a fibroadenoma, a lesion that needs analysing: Dr Zeitoun sees patients for a surgical opinion, in English. Book an appointment, or request a call back from the practice.
Understanding breast pain
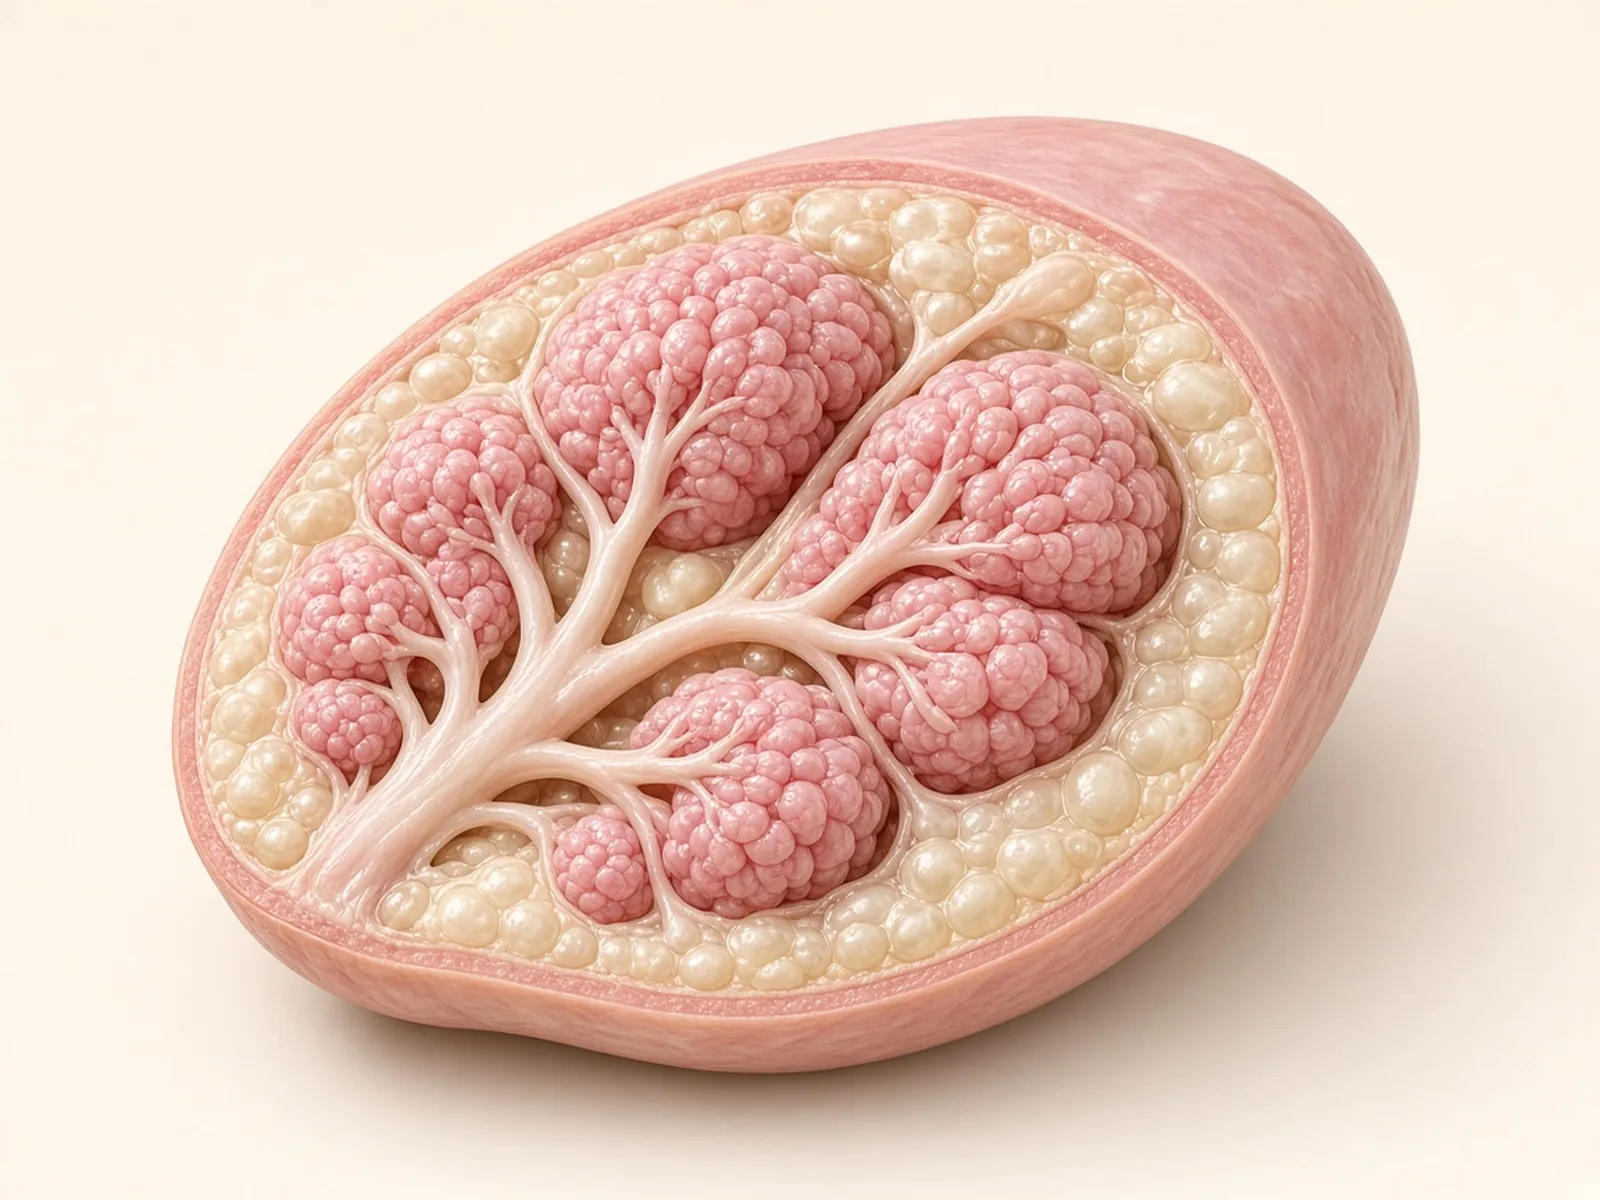
The breast responds to hormones. In the second half of the cycle it holds water, swells, and becomes tense — and it is that swelling that hurts. It also sits on a chest wall made of ribs, cartilage and muscle, crossed by nerves. Pain felt "in the breast" can therefore come from the gland, or from what lies just behind it.
Severity is not a marker of seriousness
This is what surprises patients most in consultation. Severe cyclical pain that stops you sleeping on your front, exercising or wearing certain clothes is still cyclical pain: it is disabling, not worrying. It deserves to be relieved.
Conversely, mild but new discomfort, fixed and one-sided, in a woman of 55 who is on no hormone therapy, draws more attention than violent premenstrual tenderness at 28. What counts is not what you feel: it is how the pain behaves.
Cyclical or non-cyclical?
Everything starts here. Before discussing tests at all, we establish whether the pain follows the hormonal cycle or not — because the two families differ in their causes and in what is done about them. The distinction is made during the history, in a few questions.
Cyclical pain
It appears in the second half of the cycle, peaks in the days before a period and eases once it starts. It affects both breasts, is diffuse, strongest in the upper outer quadrants, and can spread towards the armpit. It mainly concerns the reproductive years, from 20 to 50. What is done: clinical examination, and breast imaging — in practice arranged readily, including when the examination is normal.
Non-cyclical pain
It is unrelated to the cycle: sometimes constant, sometimes in flares. It often affects one breast only, in one precise spot the patient can point to. It occurs at any age, more often after 40 and after the menopause. Its causes are either within the breast or outside it — chest wall, spine, more rarely cardiac or digestive. What is done: clinical examination and targeted imaging of the painful spot, systematically.
Worth remembering. Cyclical pain can come back every month for years without meaning any disease at all. That does not mean you should keep it to yourself: see a doctor whenever you are worried — your general practitioner, your midwife or your gynecologist. Pain that changes character, becomes one-sided and fixed, appears after the menopause without hormone therapy, or comes with another sign, calls in addition for a prompt opinion.
The causes of breast pain
The breast is not always to blame. A substantial share of pain attributed to it in fact comes from what surrounds it: the chest wall, the ribs, the spine, more rarely a neighbouring organ. Recognising these causes spares a great deal of unnecessary testing — and a great deal of anxiety.
Hormonal causes
Changes across the cycle
Bilateral tenderness in the second half of the cycle, sometimes from ovulation onwards. It settles with the period and returns the following month. This is the normal behaviour of a hormone-responsive gland, not a disease.
Premenstrual syndrome
For many women, breast pain is only one sign among several. It sits within a premenstrual syndrome: abdominal bloating, a passing weight gain of one to two kilos, heavy legs, irritability, disturbed sleep, sometimes migraines. All of it appears after ovulation and clears with the period.
The mechanism is the same everywhere: in the second half of the cycle, estrogen exposure is not sufficiently balanced by progesterone. Tissue holds water — in the breasts as elsewhere. It is that imbalance, rather than an excess of hormones, that is at work, and it opens a treatment option.
Hormonal contraception
The pill, an implant, a hormonal coil: breast tenderness is common early on and usually settles. If it persists, it is discussed with the prescriber — never by stopping treatment on your own.
Menopausal hormone therapy
Mastalgia that appears on hormone replacement therapy is a good reason to reconsider the dose, the molecule or the route of administration, with the doctor who prescribed it.
Pregnancy
Breast tenderness is among the very first signs of pregnancy, often before a missed period. It affects both breasts and comes with an increase in size.
Perimenopause
Cycles become irregular and hormone levels swing more widely: pain can intensify for a few years before disappearing after the menopause.
Some medicines
The Canadian clinical guideline lists them [9]. Three families recur: antidepressants and antipsychotics (sertraline and other serotonin reuptake inhibitors, venlafaxine, mirtazapine, tricyclics, haloperidol, risperidone, phenothiazines), cardiovascular medicines (spironolactone, methyldopa, digoxin), and hormonal treatments (estrogens, progestogens, oral contraceptives, menopausal therapy, clomiphene).
For many of them the mechanism is the same: they raise prolactin. That is why your current medication list is asked for in consultation — and why a prolactin blood test is sometimes useful.
Causes within the breast itself
Fibrocystic change
By far the leading cause of painful, lumpy-feeling breasts. It is not a disease: it is the way breast tissue varies under hormonal influence. It is not operated on. It does make examination and mammographic reading harder, which sometimes justifies further imaging. Benign breast conditions →
A cyst under tension
A cyst is a pocket of fluid. When it fills quickly it puts the gland under tension and causes focal pain that can be sharp and sudden. It is one of the few causes where a simple procedure — aspiration under ultrasound — brings immediate relief.
Fibroadenoma
A benign solid tumour, typical of younger women. Usually painless, it becomes tender premenstrually in some patients. Whether to remove it is decided on grounds other than pain. Should a fibroadenoma be removed? →
Duct ectasia
A benign widening of the ducts behind the nipple. It combines pain behind the areola and, often, a thick discharge. When discharge accompanies the pain, the page to read is nipple discharge.
Mastitis and abscess
Lactational mastitis is the best known: a red, hot, tense breast with fever. Mastitis also occurs outside breastfeeding. An established abscess needs draining, sometimes surgically, and is never a matter for watchful waiting.
Inflammatory breast cancer
This is the one situation where pain and cancer genuinely meet. Over days to weeks, spreading redness, warmth, swelling and an orange-peel appearance of the skin set in. It does not resemble ordinary mastalgia and calls for an immediate consultation. Breast cancer: the guide →
Causes that do not come from the breast
Two of them are common and worth looking for at every consultation: the chest wall and bra support. The others are rare, even exceptional — they are considered when the picture resembles nothing else.
The chest wall
Tietze syndrome and costochondritis: the pain is reproduced exactly by pressing on the junction between cartilage and breastbone, and made worse by coughing or deep breathing. The pain is in the wall, not in the gland.
Bra support
An ill-fitting bra — very common — is enough on its own to keep discomfort going. It is the simplest cause to correct, and the most consistently overlooked.
Very large breasts also take their toll, but mainly through pain in the back, neck and shoulders rather than in the breasts themselves.
Spine and nerve pain
Wear and tear in the neck or upper back, or irritation of an intercostal nerve, can project a band of pain towards the breast area. This is a rare cause, considered only when the pain follows a clear path and changes markedly with position.
Shingles
Intense burning in a precise band of skin, a few days before the blisters appear. Before the rash, the diagnosis is difficult and is often made after the event.
Mondor disease
Thrombosis of a superficial vein of the breast: a hard, tender cord appears under the skin. It is rare and runs a benign course, but it warrants an examination to rule out an underlying lesion.
Cardiac or digestive origin
Crushing left-sided chest pain is not breast pain until proven otherwise. Acid reflux, or gallbladder trouble on the right, can also project onto the breast area.
Left breast, right breast, nipple: the particular cases
- →Pain in the left breast. This is the site that worries people most, for a reason that has nothing to do with the breast: the heart is close by. Crushing, pressing pain that spreads to the jaw, shoulder or left arm, comes on with exertion, with breathlessness, sweating or faintness, is not breast pain — call the emergency services immediately (15 or 112 in France).
- →Pain in the right breast. The reasoning is exactly the same. The only difference concerns neighbouring organs — the gallbladder in particular, when the pain sits under the right breast and comes on after meals.
- →Nipple pain. The nipple is richly supplied with nerves, so passing tenderness is ordinary before a period, at ovulation, in early pregnancy, while breastfeeding, or simply from clothing rubbing during sport. What is not ordinary: a spontaneous discharge, crusting or eczema that will not heal, or a recent retraction of the nipple. Nipple discharge →
- →Breast and armpit pain. Breast tissue normally extends up towards the armpit, so cyclical pain can be felt there without meaning anything. A hard, fixed, persistent node is a different matter and must be examined.
When to see a doctor, and who
Whenever you are worried. That is the main message of this page, and it applies to all breast pain, including the most ordinary. Your first port of call is the doctor you already see: your general practitioner, your midwife or your gynecologist. They examine you, arrange the imaging and refer you on if needed. Pain that worries you is reason enough to be seen — you do not have to wait until it "deserves" an appointment.
The seven situations below do not mean "cancer". They mean "to be examined without waiting several months", and most often with a specialist opinion: they are not the only reasons to consult, they are the ones that cannot be put off.
To be examined without delay
- 1The pain comes with a lump you can feel under your fingers, however small, however mobile. Breast lump: should you worry? →
- 2The pain is always in the same place, in one breast, unrelated to the cycle, and has lasted more than two cycles.
- 3Fluid comes from the nipple on its own, on one side, particularly if it is bloodstained or clear. Nipple discharge →
- 4The skin or the nipple has changed: retraction, dimpling, an orange-peel appearance, eczema that will not heal.
- 5The breast has become red, hot and swollen over a few days, with or without fever.
- 6The pain has appeared after the menopause, without any hormone therapy.
- 7A hard node has appeared under the arm and is not going away.
And one situation that is not a breast matter but an emergency: crushing chest pain spreading to the arm or jaw, with breathlessness or faintness — call 15 or 112.
Worth keeping in mind. These seven signs are not a list of cancer symptoms, and they are not the conditions you must meet before you are allowed to consult. See a doctor whenever you are worried, starting with your general practitioner, your midwife or your gynecologist. In the great majority of cases a benign cause is found — a cyst, fibrocystic change, a chest wall origin — and the consultation then serves to name the cause and relieve it.
Referred by your doctor for an opinion?
Review of your imaging, clinical examination, a clear answer on what should happen next — and a full discussion if surgery comes into question. Book an appointment, or request a call back.
The work-up for breast pain

All breast pain is investigated. None is dismissed with a "there is nothing there": even typical cyclical pain, even bilateral, even in a young woman, gets a full clinical examination and, in the great majority of cases, breast imaging. What differs from one patient to the next is not whether we investigate — it is which tests, and who takes over afterwards.
The work-up always follows the same order, in four steps. Each is set out in detail below.
The history
How long, one side or both, tied to the cycle or not, one precise spot or diffuse, reproduced by pressure. Then current medication, contraception and family history. It accounts for more than half the diagnosis.
The clinical examination
Inspection of both breasts with arms raised then lowered, palpation quadrant by quadrant, palpation of the lymph node areas, checking for discharge — and palpation of the chest wall, often forgotten, which unmasks a chest wall origin.
Mammogram and ultrasound
This is the backbone of the work-up, arranged readily. Mammography together with ultrasound after 40; ultrasound alone first in younger women. The report grades what is seen from BI-RADS 1 to 6.
Core needle biopsy
Only if imaging has shown something: we never biopsy pain, we biopsy an image. It is performed by the radiologist under ultrasound guidance and local anaesthetic, leaving a tiny clip that marks the target.

Steps 1 and 2 · What happens in consultation

Consultations take place either at the practice at 241 rue du Faubourg Saint-Honoré, Paris 8th, or at Clinique Hartmann in Neuilly-sur-Seine — both are consulting sites. Surgery is carried out at Clinique Hartmann only.
Bring your previous imaging — reports and films. It is the one document that genuinely helps: it allows comparison and often saves a consultation.
The examination always ends with the chest wall, with the patient lying on her side. This is the step that settles a great many diagnoses: when pressing on the cartilage reproduces the pain exactly, it is not coming from the gland.
Step 3 · The mammogram
After 40, the mammogram is the reference test, arranged even when the clinical examination is normal. Two views per breast, completed where needed by tomosynthesis, which rebuilds the breast in thin slices and separates overlapping tissue.
It is targeted on the painful area when the pain is focal, and covers both breasts when it is diffuse. The radiologist issues a report graded BI-RADS: 1 and 2 normal or benign, 3 probably benign with a short-interval follow-up, 4 and 5 suspicious, calling for a biopsy.
Understanding your mammogram → · Understanding the BI-RADS score →
Step 3 (continued) · The ultrasound

Ultrasound systematically completes the mammogram, and it is the first test in younger women, whose breast tissue is dense. Painless and free of X-rays, it is passed directly over the painful spot you point to.
It settles the commonest question of all: is the lesion fluid-filled — a cyst, which can be aspirated and relieved on the spot — or solid, which leads to characterising it and then, depending on its appearance, sampling it?
Step 4 · The core needle biopsy
It comes only at the end of the chain, and only for a lesion graded BI-RADS 4 or 5. The radiologist takes a few small cores with a needle, under ultrasound guidance and local anaesthetic, in about thirty minutes. A tiny clip is left in place to mark the target should surgery follow.
The samples go to the pathology laboratory. The result comes back within a few days and is explained in consultation — never announced by telephone or email. Understanding the pathology report →
A hormone blood test — prolactin, thyroid function, a review of medication — is added when the pain is clearly cyclical and accompanied by a premenstrual syndrome. Breast MRI, on the other hand, has no place in the work-up of isolated breast pain.
When is surgery needed?

Pain itself is never operated on. What is removed is an identified lesion — and that is exactly why the work-up matters: it separates the very large majority of situations that need no procedure from the few that do. Here are those situations.
A large, recurrent cyst
A cyst under tension is aspirated first under ultrasound: a simple outpatient procedure that relieves the pain immediately. Removal is discussed only for closely spaced, highly symptomatic recurrences, or for a complex cyst that needs analysing.
A symptomatic fibroadenoma
Removal is discussed for documented growth, significant size, constant discomfort, or doubt about a phyllodes tumour. A biopsy is performed before any surgery, even when the imaging appearance is typical. The fibroadenoma page →
A breast abscess
A collected abscess does not resolve on antibiotics alone. It is drained — by ultrasound-guided aspiration where possible, surgically when the collection is large or divided into pockets.
An intraductal papilloma
For pathological nipple discharge caused by a papilloma, limited surgery on the affected duct segment both treats the problem and provides the diagnosis. Nipple discharge →
A high-risk (B3) lesion
Atypical hyperplasia, a radial scar, a lesion graded B3: these do not explain the pain, but they are sometimes found during the work-up and call for removal and closer surveillance. High-risk lesions →
A malignant lesion
Rare, but possible. Management is then that of breast cancer, decided in a multidisciplinary team meeting, with every option discussed before any decision is taken.
How the decision is made
- →Consultations take place at the practice at 241 rue du Faubourg Saint-Honoré, Paris 8th, and at Clinique Hartmann in Neuilly-sur-Seine. Surgery is carried out at Clinique Hartmann only.
- →Every risk is explained in consultation, and a written quotation is provided before any procedure. Dr Zeitoun practises in sector 2, with fees above the statutory tariff.
- →A second-opinion consultation is available before any breast surgery, including where an operation has already been proposed elsewhere.
- →Anything removed is systematically analysed in the laboratory, and the result is explained to you at a follow-up consultation.
- →Patients travelling from abroad will find the practical arrangements — written quotation, visa letters, interpreters, accommodation — on the international patients page. The consultation always comes before the journey.
A lesion to operate on, or a second opinion?
A recurrent cyst, a fibroadenoma, a high-risk lesion, or surgery already proposed elsewhere: a surgical opinion and, if needed, day surgery at Clinique Hartmann. Book an appointment, or request a call back.
What actually helps
The measures below apply to pain whose cause has been established as benign after examination. They do not replace a consultation, and none of them should lead you to change a current treatment on your own.

The bra, before anything else
Proper support clearly reduces pain in most women who consult for mastalgia. Two things matter: the actual size, which is not the one you have been buying for ten years, and support during sport. In very painful phases, a wire-free night bra brings real benefit.
It is the simplest measure, the cheapest — and the most consistently overlooked.
Simple painkillers
Paracetamol first. An anti-inflammatory gel applied to the painful area is particularly useful for focal and chest wall pain, with the advantage of avoiding systemic exposure. Oral anti-inflammatories are used for short periods and on medical advice.
Balancing progesterone and estrogen
This is the standard French approach to established cyclical mastalgia, particularly when it comes with a premenstrual syndrome. The reasoning is simple: since the pain arises from estrogen exposure that is insufficiently balanced in the second half of the cycle, progesterone is given to restore the balance.
Two routes exist. Topically, as a progesterone gel applied to the breasts, acting locally with no systemic effect. Orally, as micronised progesterone or a progestogen, typically from around day 15 to day 25 of the cycle, which also helps the other premenstrual symptoms. The choice, the duration and the monitoring are for the prescribing doctor: this is a prescription, not self-medication.
Hormone treatment already in place
Mastalgia that appeared with contraception or with menopausal hormone therapy is worth raising with the doctor who prescribed it: changing the molecule, the dose or the route often settles the problem. Never stop a treatment on your own initiative.
Caffeine, tobacco, lifestyle
Cutting down on caffeine is very often advised. It is worth being honest about the evidence: studies conflict, and the benefit, where it exists, is modest. It remains a simple, risk-free trial over two or three cycles. Stopping smoking and regular physical activity have well-established benefits on other grounds.
The limits
No food supplement has shown solid efficacy against breast pain. Specific hormonal treatments for mastalgia exist but carry real side effects: they are reserved for severe, disabling, resistant forms, on prescription and under supervision.
A case apart: pain after breast surgery
After a lumpectomy, a mastectomy, an axillary clearance or a breast reconstruction, pain, pulling, burning or shooting sensations can persist for several months. They do not mean recurrence, nor that the operation failed: they most often reflect involvement of the small nerve branches in the area.
Specific treatments exist, and they work better the earlier they are started. This pain should not be endured in silence until the next follow-up appointment: it should be described, assessed and treated.
Imaging already done?
Dr Jérémie Zeitoun, surgical oncologist and breast surgeon, sees patients at the practice at 241 rue du Faubourg Saint-Honoré (Paris 8e) and at Clinique Hartmann (Neuilly-sur-Seine). The consultation places the pain and decides whether further tests are needed.
Frequently asked questions
The questions that come up most often about breast pain. If yours is not here, ask it at your appointment — or ask Sophie, the practice assistant, at the bottom right of the screen.
Is breast pain serious?
Almost never. On its own, breast pain is not a sign of breast cancer: in published series, cancer is found in 2 to 7% of women who consult for it, and when pain is the only symptom that figure falls to 0.8% in a Canadian series of 953 patients and to 0.4% in a British cohort of 10,830 women — the same level as in a screened population with no symptoms at all. What matters is not how severe the pain is, but how it behaves.
Does breast cancer hurt?
Usually not. The great majority of breast cancers are found as a painless lump, as an abnormality on a screening mammogram, or through a change in the skin or the nipple. One form is the exception: inflammatory breast cancer (see the breast cancer page), which over days to weeks combines spreading redness, warmth, swelling and an orange-peel appearance of the skin. That situation calls for an immediate consultation.
When should I see a doctor about breast pain, and who?
Whenever you are worried. Breast pain that concerns you is reason enough to be seen, even if it seems ordinary. Your first port of call is your general practitioner, your midwife or your gynecologist: they examine you, arrange the imaging and refer you on if needed to a breast surgeon. Book an appointment →
Some situations cannot be put off and call for a prompt opinion: pain with a lump, pain always in the same spot in one breast for more than two cycles, nipple discharge, skin or nipple changes, a breast that becomes red, hot and swollen, pain appearing after the menopause without hormone therapy, or a hard node under the arm.
Why do my breasts hurt before my period?
This is cyclical mastalgia, the commonest form. Under the hormonal changes of the second half of the cycle, glandular tissue retains fluid and becomes tense and tender. The pain affects both breasts, is strongest in the upper outer quadrants, can spread towards the armpit, and eases once the period begins. Severe cyclical pain is still cyclical pain: severity is not a marker of seriousness.
Can pain in the left breast come from the heart?
Yes, which is why left-sided chest pain should never be dismissed. Crushing, pressing pain that spreads to the jaw, shoulder or left arm, comes on with exertion and is accompanied by breathlessness, sweating or faintness is not breast pain: call the emergency services at once — 15 or 112 in France. Superficial pain that is reproduced by pressing on the spot and varies with position points instead to the chest wall or to the breast itself.
What tests are done for breast pain?
All breast pain is investigated. The history first, then a full clinical examination including palpation of the chest wall. Breast imaging is then arranged in the great majority of cases — targeted on the painful spot when the pain is focal, covering both breasts when it is diffuse: ultrasound first in younger women, mammography with ultrasound after 40. A biopsy is performed only for a lesion graded BI-RADS 4 or 5.
Is breast pain ever treated with surgery?
Pain itself is never operated on: what is removed is an identified lesion. Surgery is discussed for a large, recurrent and highly symptomatic cyst, a growing or bulky fibroadenoma, a breast abscess that needs draining, pathological nipple discharge with an intraductal papilloma, a high-risk (B3) lesion found during the work-up, or, more rarely, a malignant lesion. The decision is made after the full work-up, in consultation, case by case.
What actually relieves breast pain?
A properly fitted supportive bra, worn at night during painful phases, is the most effective and most overlooked measure. Depending on the situation, add paracetamol, an anti-inflammatory gel applied locally, and, for clearly cyclical pain with premenstrual symptoms, progesterone in the second half of the cycle to balance estrogen exposure. Any hormone treatment already in place is reviewed with the doctor who prescribed it, never stopped on your own. Aspiration under ultrasound relieves a tense cyst immediately.
What are Dr Zeitoun’s fees?
Dr Zeitoun practises in Sector 2 (non-OPTAM) and charges fees above the French Social Security rate for all consultations and procedures. Most international patients are not covered by French Social Security. A detailed quote is given during the consultation, before any procedure. If you are covered, the Assurance Maladie reimburses on the basis of the Social Security rate, and your health insurance may cover all or part of the additional fees, depending on your policy.
Read also
To go further on the other breast symptoms and on the work-up.
You have felt a lump: what is reassuring, what should prompt a consultation, and how the work-up unfolds.
Fluid or blood coming from the nipple: what is benign, what must be investigated, and when surgery is needed.
Benign and high-risk breast lesions: which are simply monitored, and which are removed.
The first-line test for focal pain in younger women: how it works, what it shows, what it settles.
Tomosynthesis, the BI-RADS score, breast density, and how to read the report.
Written quotation, visa letters, interpreters, accommodation and discretion for patients travelling to Paris.
A breast finding to operate on, or to review?
For pain, start with your general practitioner, your midwife or your gynecologist. If their examination or your imaging finds a lump, a cyst, a fibroadenoma or an image that needs analysing, Dr Jérémie Zeitoun, surgical breast oncologist, sees patients at the practice in the 8th arrondissement of Paris and at Clinique Hartmann in Neuilly-sur-Seine, where he also operates. Consultations in English and French.
You would rather not wait?
The practice arranges the appointment in Paris 8e or at Clinique Hartmann. When an operation is decided, it takes place at Clinique Hartmann.
Dr Zeitoun practises in Sector 2 (non-OPTAM) and charges fees above the French Social Security rate for all consultations and procedures. Most international patients are not covered by French Social Security. A detailed quote is given during the consultation, before any procedure. If you are covered, the Assurance Maladie reimburses on the basis of the Social Security rate, and your health insurance may cover all or part of the additional fees, depending on your policy.
Sources
Every figure quoted in this article refers to the numbered references below.
- 1Cornell LF, Sandhu NP, Pruthi S, Mussallem DM. Current Management and Treatment Options for Breast Pain. Mayo Clinic Proceedings 2020;95(3):574-580 — lifetime prevalence of breast pain (around 70%) and proportion of cancers among women consulting for it (2 to 7%).
- 2Mohallem Fonseca M et al. Breast pain and cancer: should we continue to work-up isolated breast pain? Breast Cancer Research and Treatment 2019 — series of 953 patients, cancer detection rate of 0.8% for isolated breast pain, comparable to the expected incidence in asymptomatic women.
- 3Prospective British cohort, British Journal of General Practice 2022;72(717) — 10,830 women referred to a breast clinic: cancer incidence of 0.4% for isolated breast pain, against around 5% for a breast lump.
- 4Duijm LEM et al. Value of breast imaging in women with painful breasts. BMJ 1998 — normal or benign imaging in 95% of women investigated for breast pain; cancer prevalence identical to that of controls.
- 5ACR Appropriateness Criteria® — Breast Pain, American College of Radiology — criteria for choosing imaging according to age and to whether the pain is focal or diffuse.
- 6SFSPM — French Society of Senology and Breast Pathology, SENORIF 2025-2026 guidelines on benign and borderline breast disease.
- 7CNGOF — French College of Gynaecologists and Obstetricians: clinical practice guidelines on benign breast disease and premenstrual syndrome.
- 8HAS and INCa — French National Authority for Health and French National Cancer Institute: early detection of breast cancer and management of breast abnormalities (has-sante.fr, e-cancer.fr).
- 9Rosolowich V et al. Mastalgia — clinical practice guideline of the Society of Obstetricians and Gynaecologists of Canada. Journal of Obstetrics and Gynaecology Canada 2006;28(1):49-71 — table of medicines associated with mastalgia, reproduced since in practice guides.
This page is provided for general information. It is not medical advice and does not replace a consultation. No opinion can be given without an in-person examination and a full review of your medical file.